
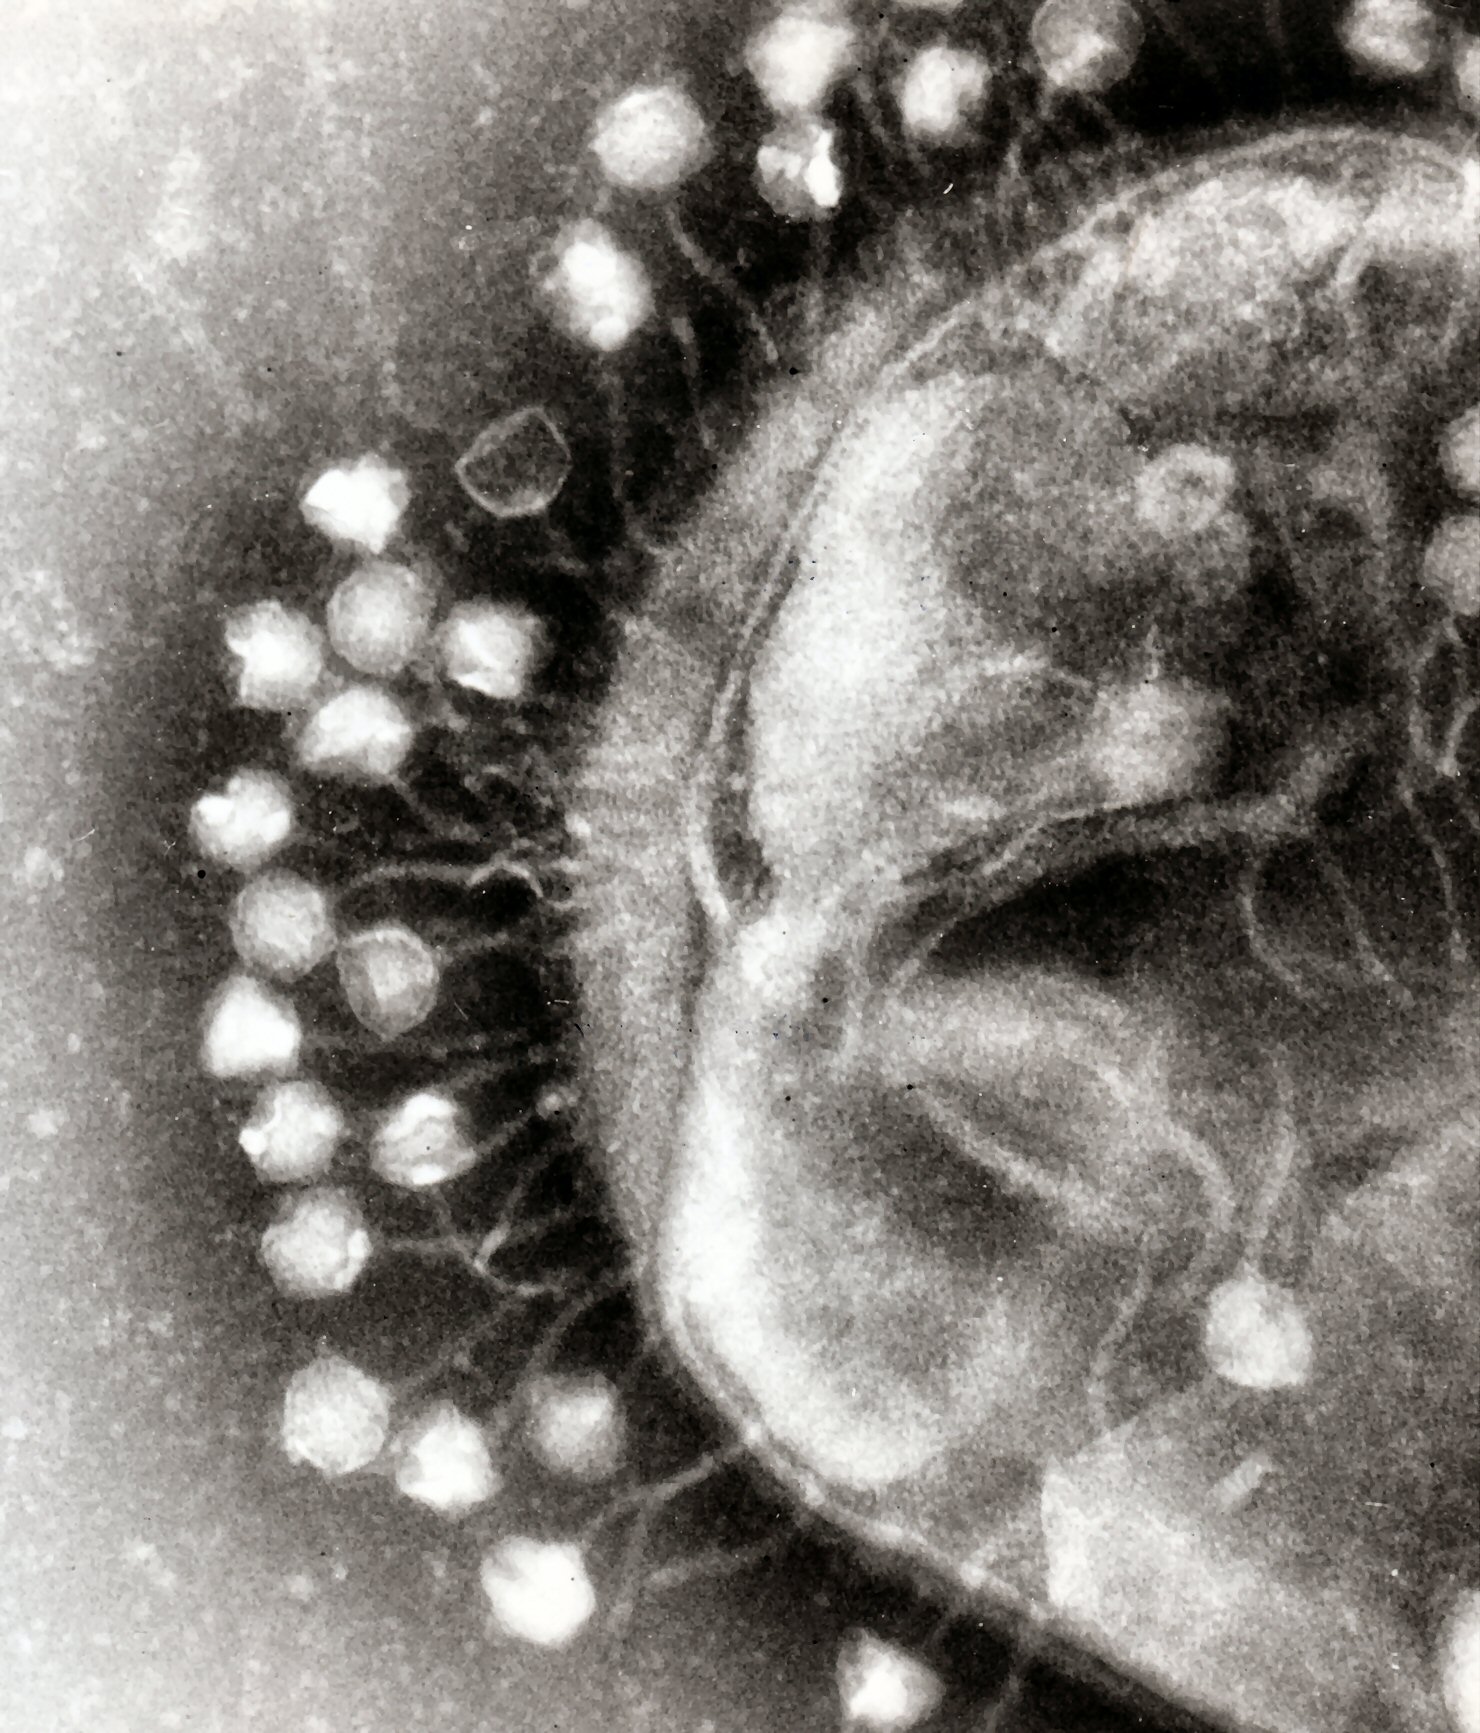
Antibiotic-resistant infections may soon have a more carefully mapped route to an experimental alternative: viruses engineered by nature to hunt bacteria. An international working group has produced the first coordinated clinical framework for personalized phage therapy, an approach that matches bacteria-killing bacteriophages to an individual patient’s infection.
Led by the German Society for Infectious Diseases, the effort brings together 18 international experts, 20 professional societies, patient advocates, and regulatory authorities. Published in Nature Medicine, the consensus document contains more than 60 recommendations covering phage selection, laboratory testing, manufacturing, quality control, administration, monitoring, documentation, and future research. The journal’s publication record describes the guidelines as a framework for moving individualized treatment toward clinical use.
Phages are viruses that infect specific bacteria rather than human cells. That precision is both their appeal and their complication: unlike a broad-spectrum antibiotic, a phage may work against one bacterial strain but fail against another. Doctors therefore need laboratory testing to identify a usable virus, determine how it interacts with the patient’s bacterial isolate, and decide whether it should be administered alone or as part of a phage cocktail.
The early numbers are encouraging but not yet a license for routine use. In a Belgian case series of 100 treated patients, 77 percent showed clinical improvement, while the targeted bacteria became undetectable in 61 percent of cases. Those figures come from observational treatment, not a controlled clinical trial, so they cannot establish how much benefit came from phages, other therapies, or differences among patients. Medical Xpress’ account of the guideline likewise emphasizes that treatment decisions must remain individualized.
The recommendations call for a multidisciplinary process involving treating physicians, clinical microbiologists, and recognized phage specialists. That matters because phage therapy involves more than selecting a promising virus: preparations must be produced and tested consistently, patients must be monitored for response and possible complications, and treatment records need to support future research. The guidelines are scheduled to remain valid through June 29, 2030, with annual review built into the process.
For now, phage therapy is best understood as a potential rescue option for infections in which established treatments are ineffective, unavailable, or unsuitable—not a replacement for antibiotics in ordinary cases. The World Health Organization’s European office notes that phages may also be paired with antibiotics, including in efforts to improve treatment against resistant bacteria. The new framework’s real test will be whether standardized preparation, better patient selection, and controlled trials can turn scattered compassionate-use successes into dependable clinical practice.
Image Credits
In-Article Image Credits
Phage therapy: Transmission electron micrograph of multiple bacteriophages attached to a bacterial cell wall; the magnification is approximately 200,000 via Wikimedia Commons by Professor Graham Beards with usage type - Creative Commons License. By Professor Graham Beards - en:Image:Phage.jpg, CC BY-SA 3.0, https://commons.wikimedia.org/w/index.php?curid=5035798Featured Image Credit
Phage therapy: Transmission electron micrograph of multiple bacteriophages attached to a bacterial cell wall; the magnification is approximately 200,000 via Wikimedia Commons by Professor Graham Beards with usage type - Creative Commons License. By Professor Graham Beards - en:Image:Phage.jpg, CC BY-SA 3.0, https://commons.wikimedia.org/w/index.php?curid=5035798


